To be human is to have back pain. As one of the most common physical disorders—affecting about 90 percent of Americans at some point in their lives—back pain is also the leading cause of disability worldwide.1
Numerous theories regarding the primary cause of low-back pain have circulated over the years, including referred sacroiliac joint pain and nerve inflammation (early 1900s); “muscular rheumatism” (fibromyalgia) and psychological issues like “hysteria” (1920s–1930s); quadratus lumborum (QL) spasm (up until the 1950s); disc issues (1930s–1980s); transversus abdominis strength (1990s); multifidus size (2000s); and “core stability” (in the last decade).2 While many of these theories are important in understanding back pain, up to 85 percent of cases still have no known cause.3 Researchers have recently identified that the thoracolumbar fascia (TLF) may also contribute to low-back pain.
The Thoracolumbar Fascia’s Role in Low-Back Pain
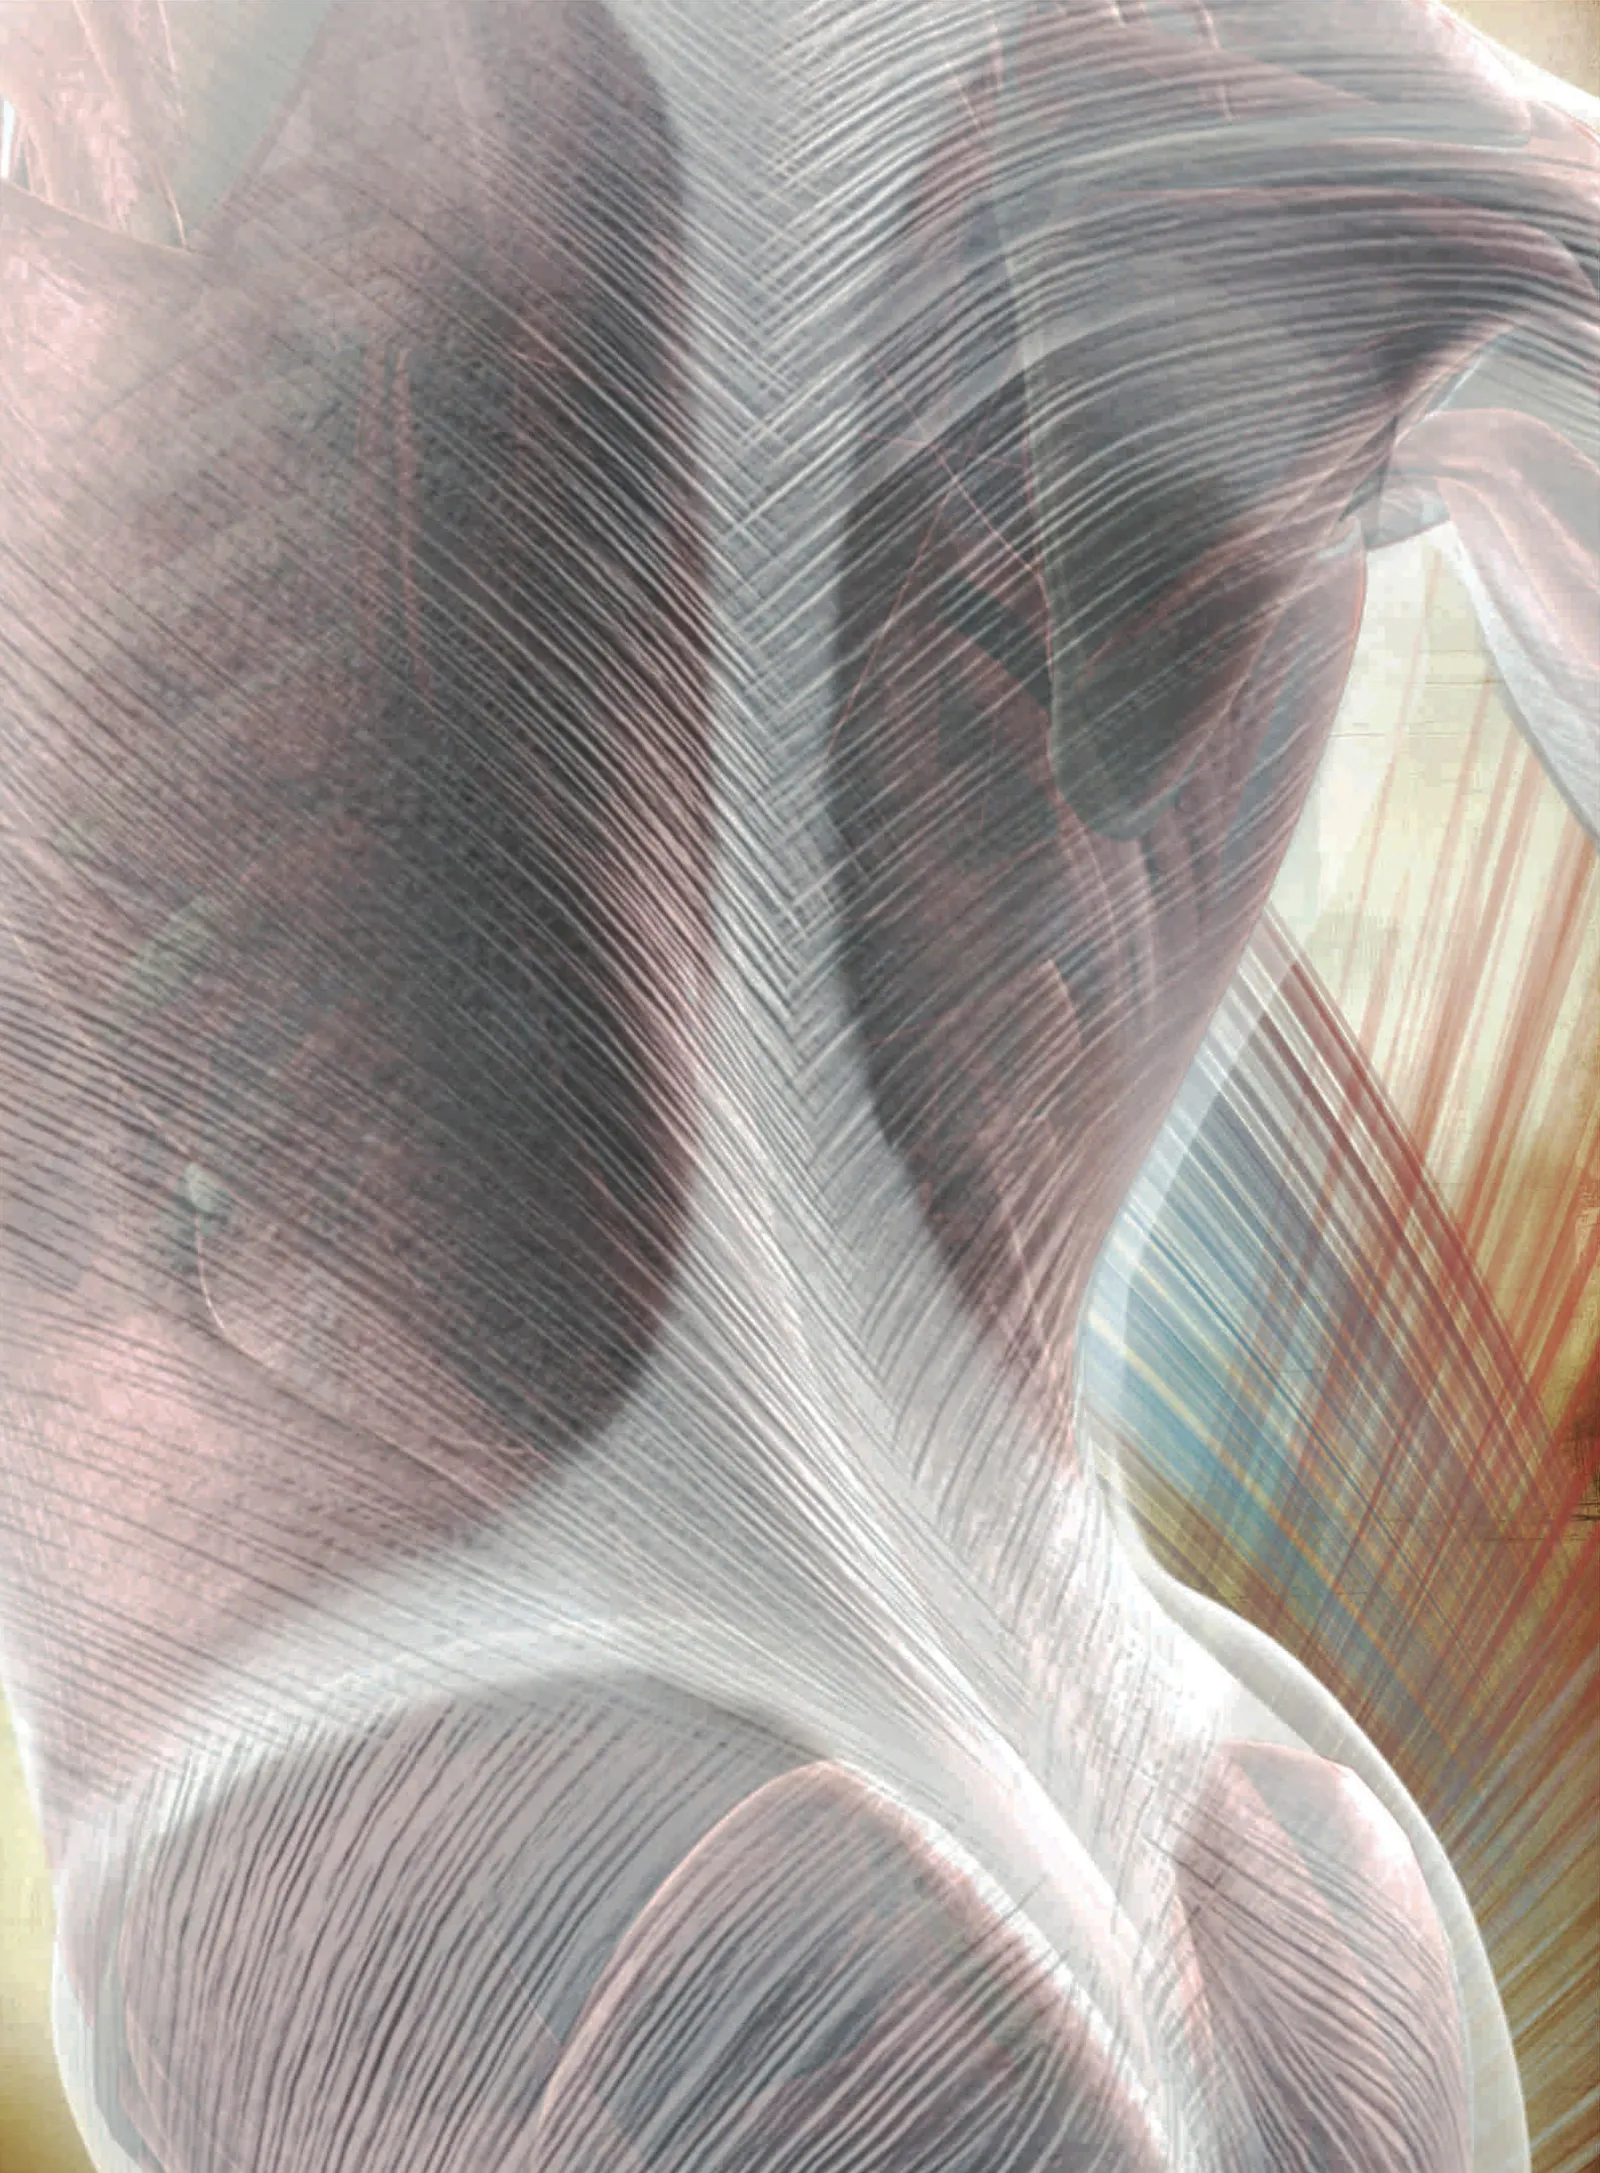
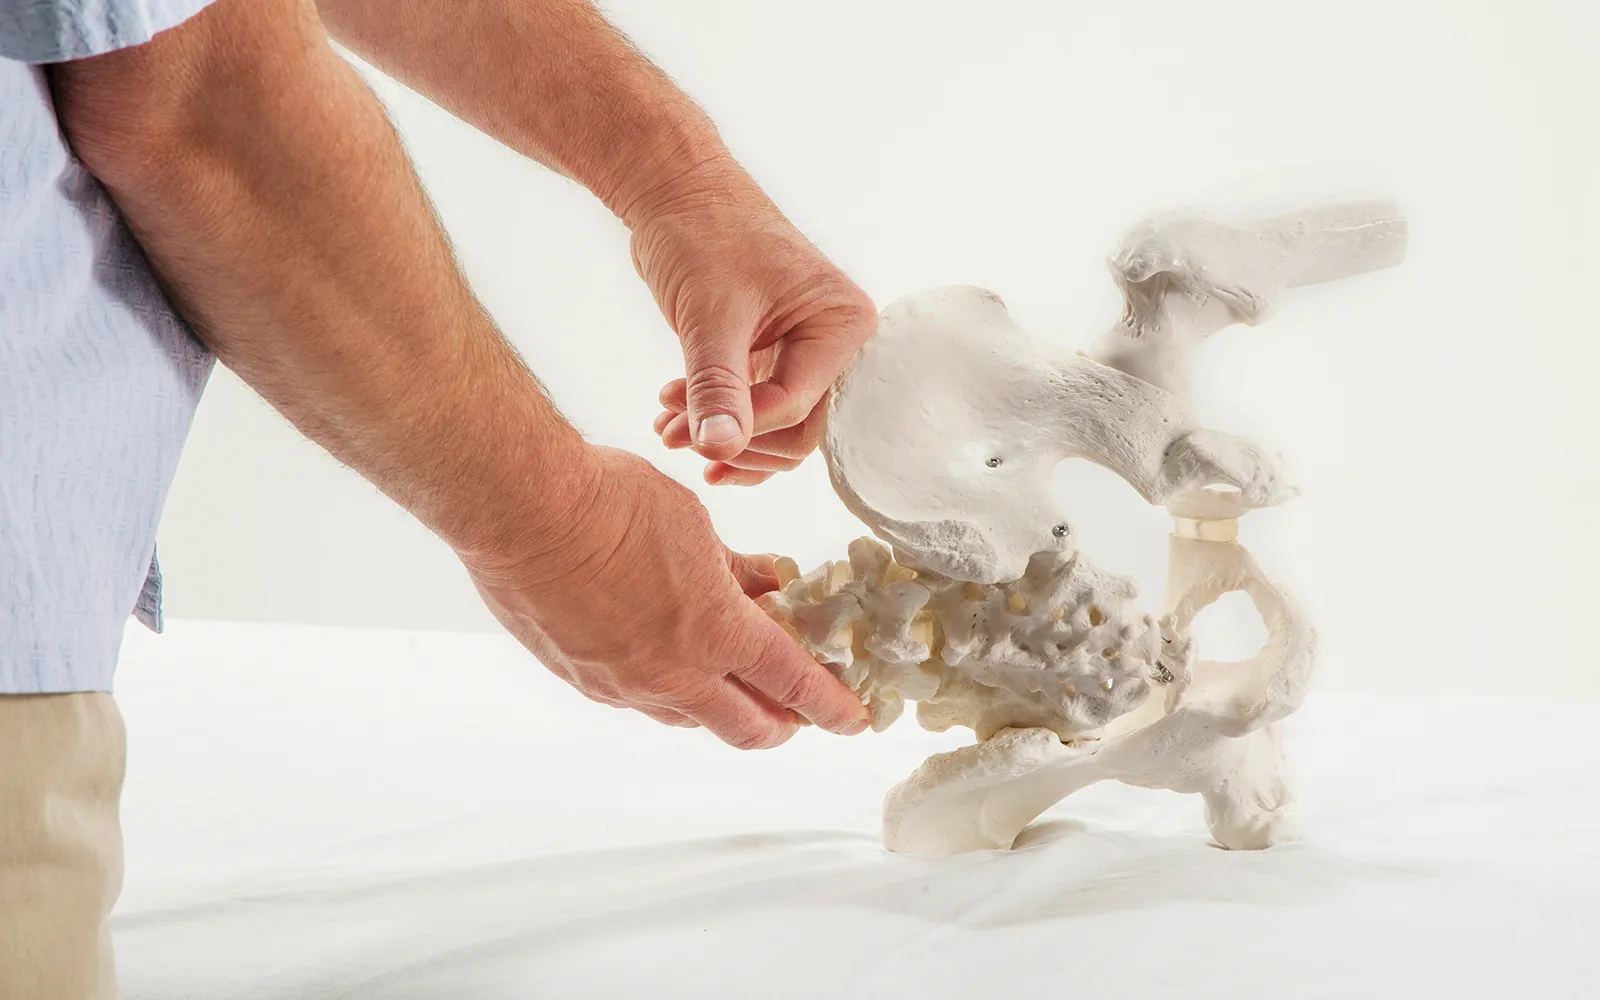
Image 1.
The TLF, or lumbodorsal fascia, covers and separates many of the muscle groupings that lie posterior to the spine. It is usually depicted as a diamond-shaped structure over the lower back, connecting the gluteal fascia to the latissimus dorsi. However, from other angles it becomes clear that this structure is much more complex. Multiple layers wrap three-dimensionally around the structures of the low back, extending from the base of the neck (where it is contiguous with the deep cervical fascia) to the sacrum and iliac crests of the pelvis. Its layers adhere to the processes of the lumbar vertebrae and spinal ligaments (along the midline of the back), and to the ribs (laterally). The TLF wraps and connects several of the structures thought to be responsible for low-back pain, such as the multifidi, QL, spinal erectors, and spinal ligaments, and it connects other muscles such as the diaphragm, obliques, and transverse abdominis.
The increasing awareness of fascia’s role in sensation and pain perception (see “Understanding Fascial Change: Continuity, Plasticity, and Sensitivity” in Massage & Bodywork, May/June 2014) has led to research showing there are numerous free nerve endings and mechanoreceptors in the back’s TLF and that it is physically different in those with low-back pain. One study showed that the TLF was significantly thicker in those with low-back pain than in those without.4 Less gliding has also been observed between the deeper layers of the TLF in people with low-back pain, suggesting that our goals of achieving fascial elasticity and layer differentiation could explain why manual therapy has helped relieve chronic back pain.5
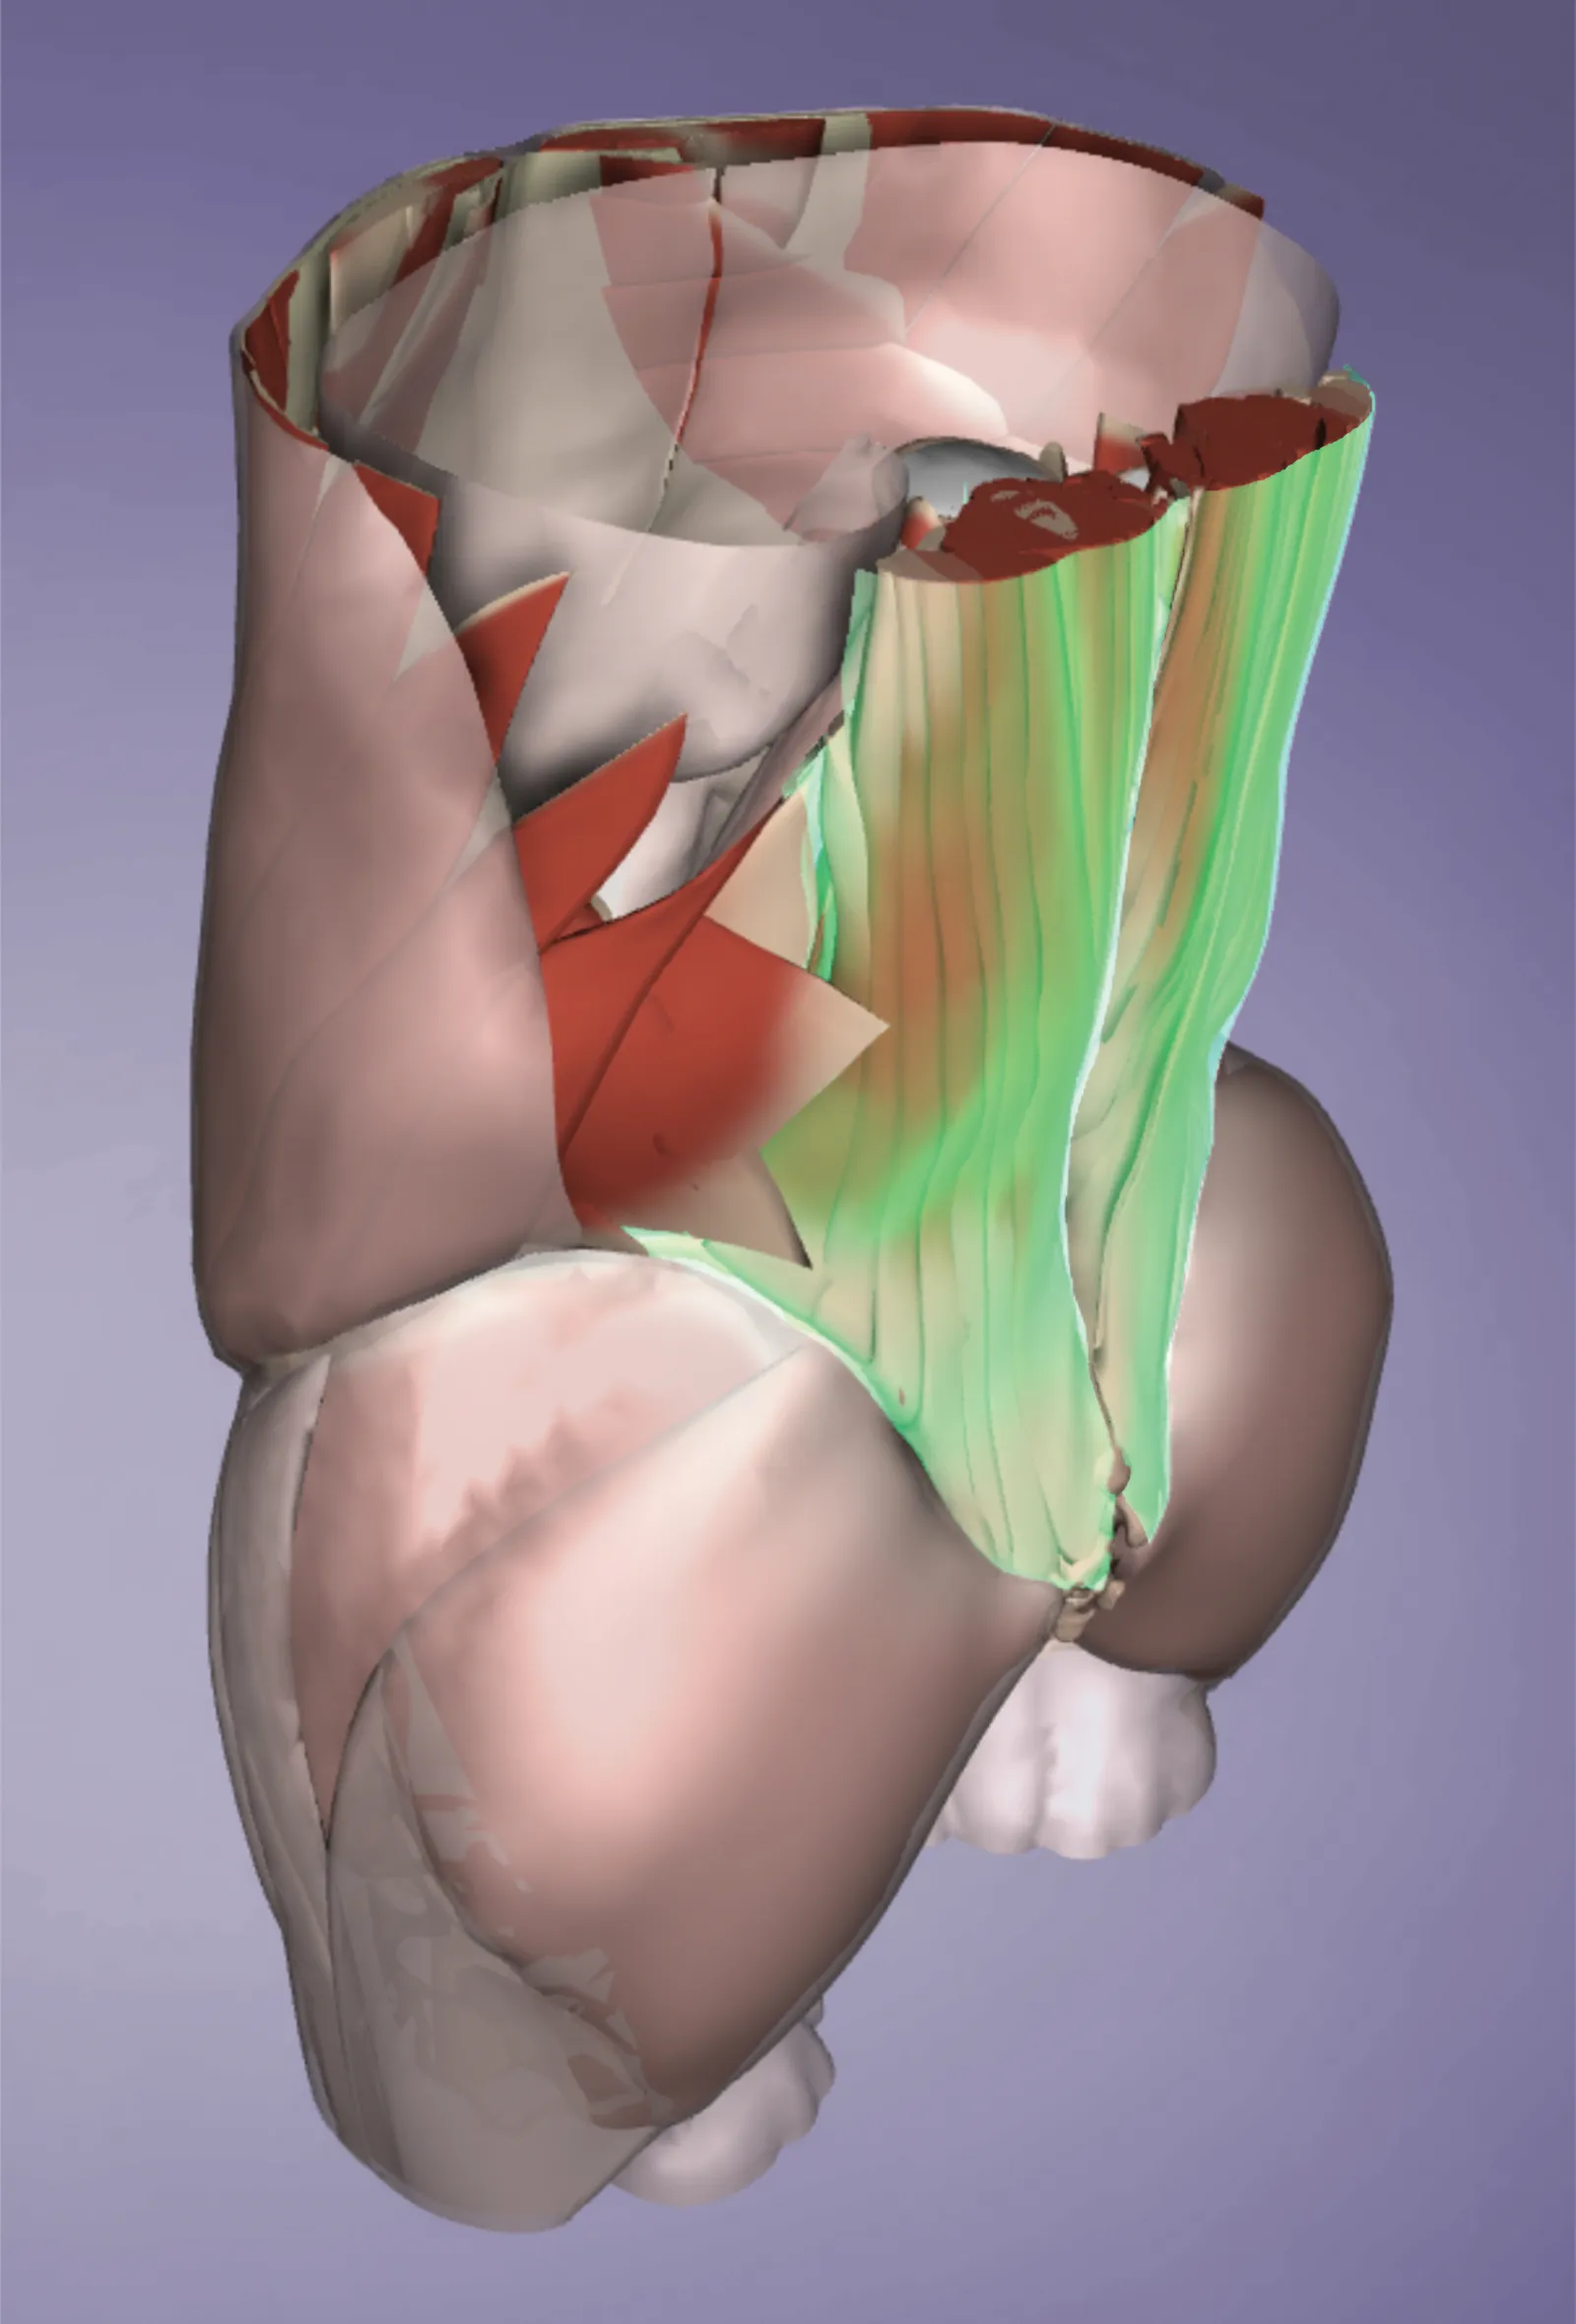
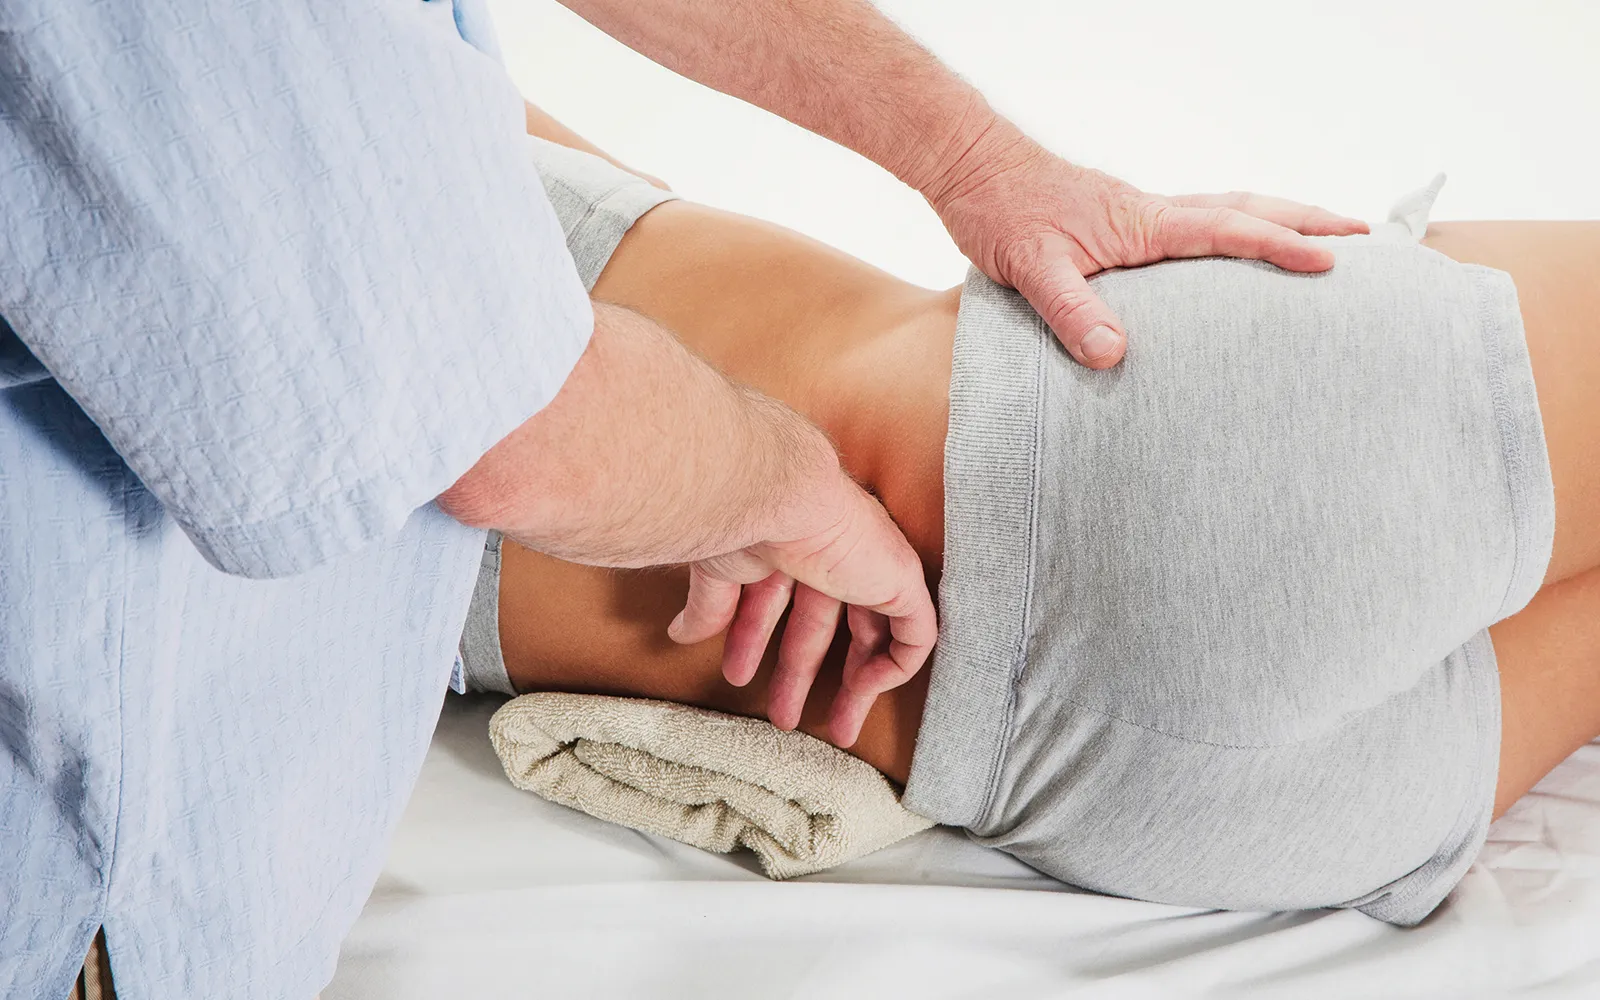
Image 2.
Because the sensitive TLF diagonally joins each leg to its opposite-side arm, it is important in the mechanical and proprioceptive control of walking, running, throwing, and all contralateral motions. As a whole-body connector it can be significantly involved in low-back pain and midback pain, recurring tightness in the thoracic spine or low back, spinal stiffness and restricted rotation/flexion, inhibited contralateral arm/leg motion, and limited rib or back motion in diaphragmatic breathing. It is also implicated in many other conditions, including hip or sacroiliac pain, plantar fasciitis, and suboccipital headaches, given its indirect fascial connections to these regions.6
Iliac Crest Technique
The TLF’s layers insert on the thin, bony ridges of the iliac crest, forming the bony attachments of the transverse abdominis, obliques, and iliocostalis— the largest and most lateral of the spinal erectors. Since we are preparing for low-back work, we’ll emphasize the superior aspect of these bony ridges where these low-back structures attach.
Using a soft fist, feel for the ridge of the iliac crest. Slightly wrap around the crest’s ridge with the furrow between two of your knuckles. On many clients with long-term low-back pain, you’ll find thick, dense fascial buildup here. Starting at the lateral-most part of the hip crest, sink in slowly, feeling for tissue softening in response. By waiting for this, we are evoking a reduction in the resting tone of the fascia’s associated muscles via a Golgi tendon organ reflex.7 This allows our work to have a much greater effect, and it helps prepare for more direct work with the lumbar sections of the TLF.
Once the tissue softens slightly in response to your static pressure, glide medially along the crest to move to a new area. Wait here for tissue softening, which will allow you to glide to the next area. As you glide along the crest, you’ll encounter the more muscular attachments of the QL and iliocostalis. Slow down. Take a more superficial layer. Continue this process of waiting for a response in each place until you’ve reached the posterior superior iliac spine. Repeat at a slightly deeper level, or perform the next technique.
Thoracolumbar Fascia Technique
The TLF is composed of dense, fibrous connective tissue layers, separated by thin layers of loose connective tissue that allow the dense layers to glide against one another during trunk motion. Less gliding between the layers has been correlated with low-back pain. We’ll address each layer of the TLF in turn, restoring differentiation and elasticity.
Superficial and Posterior Layers
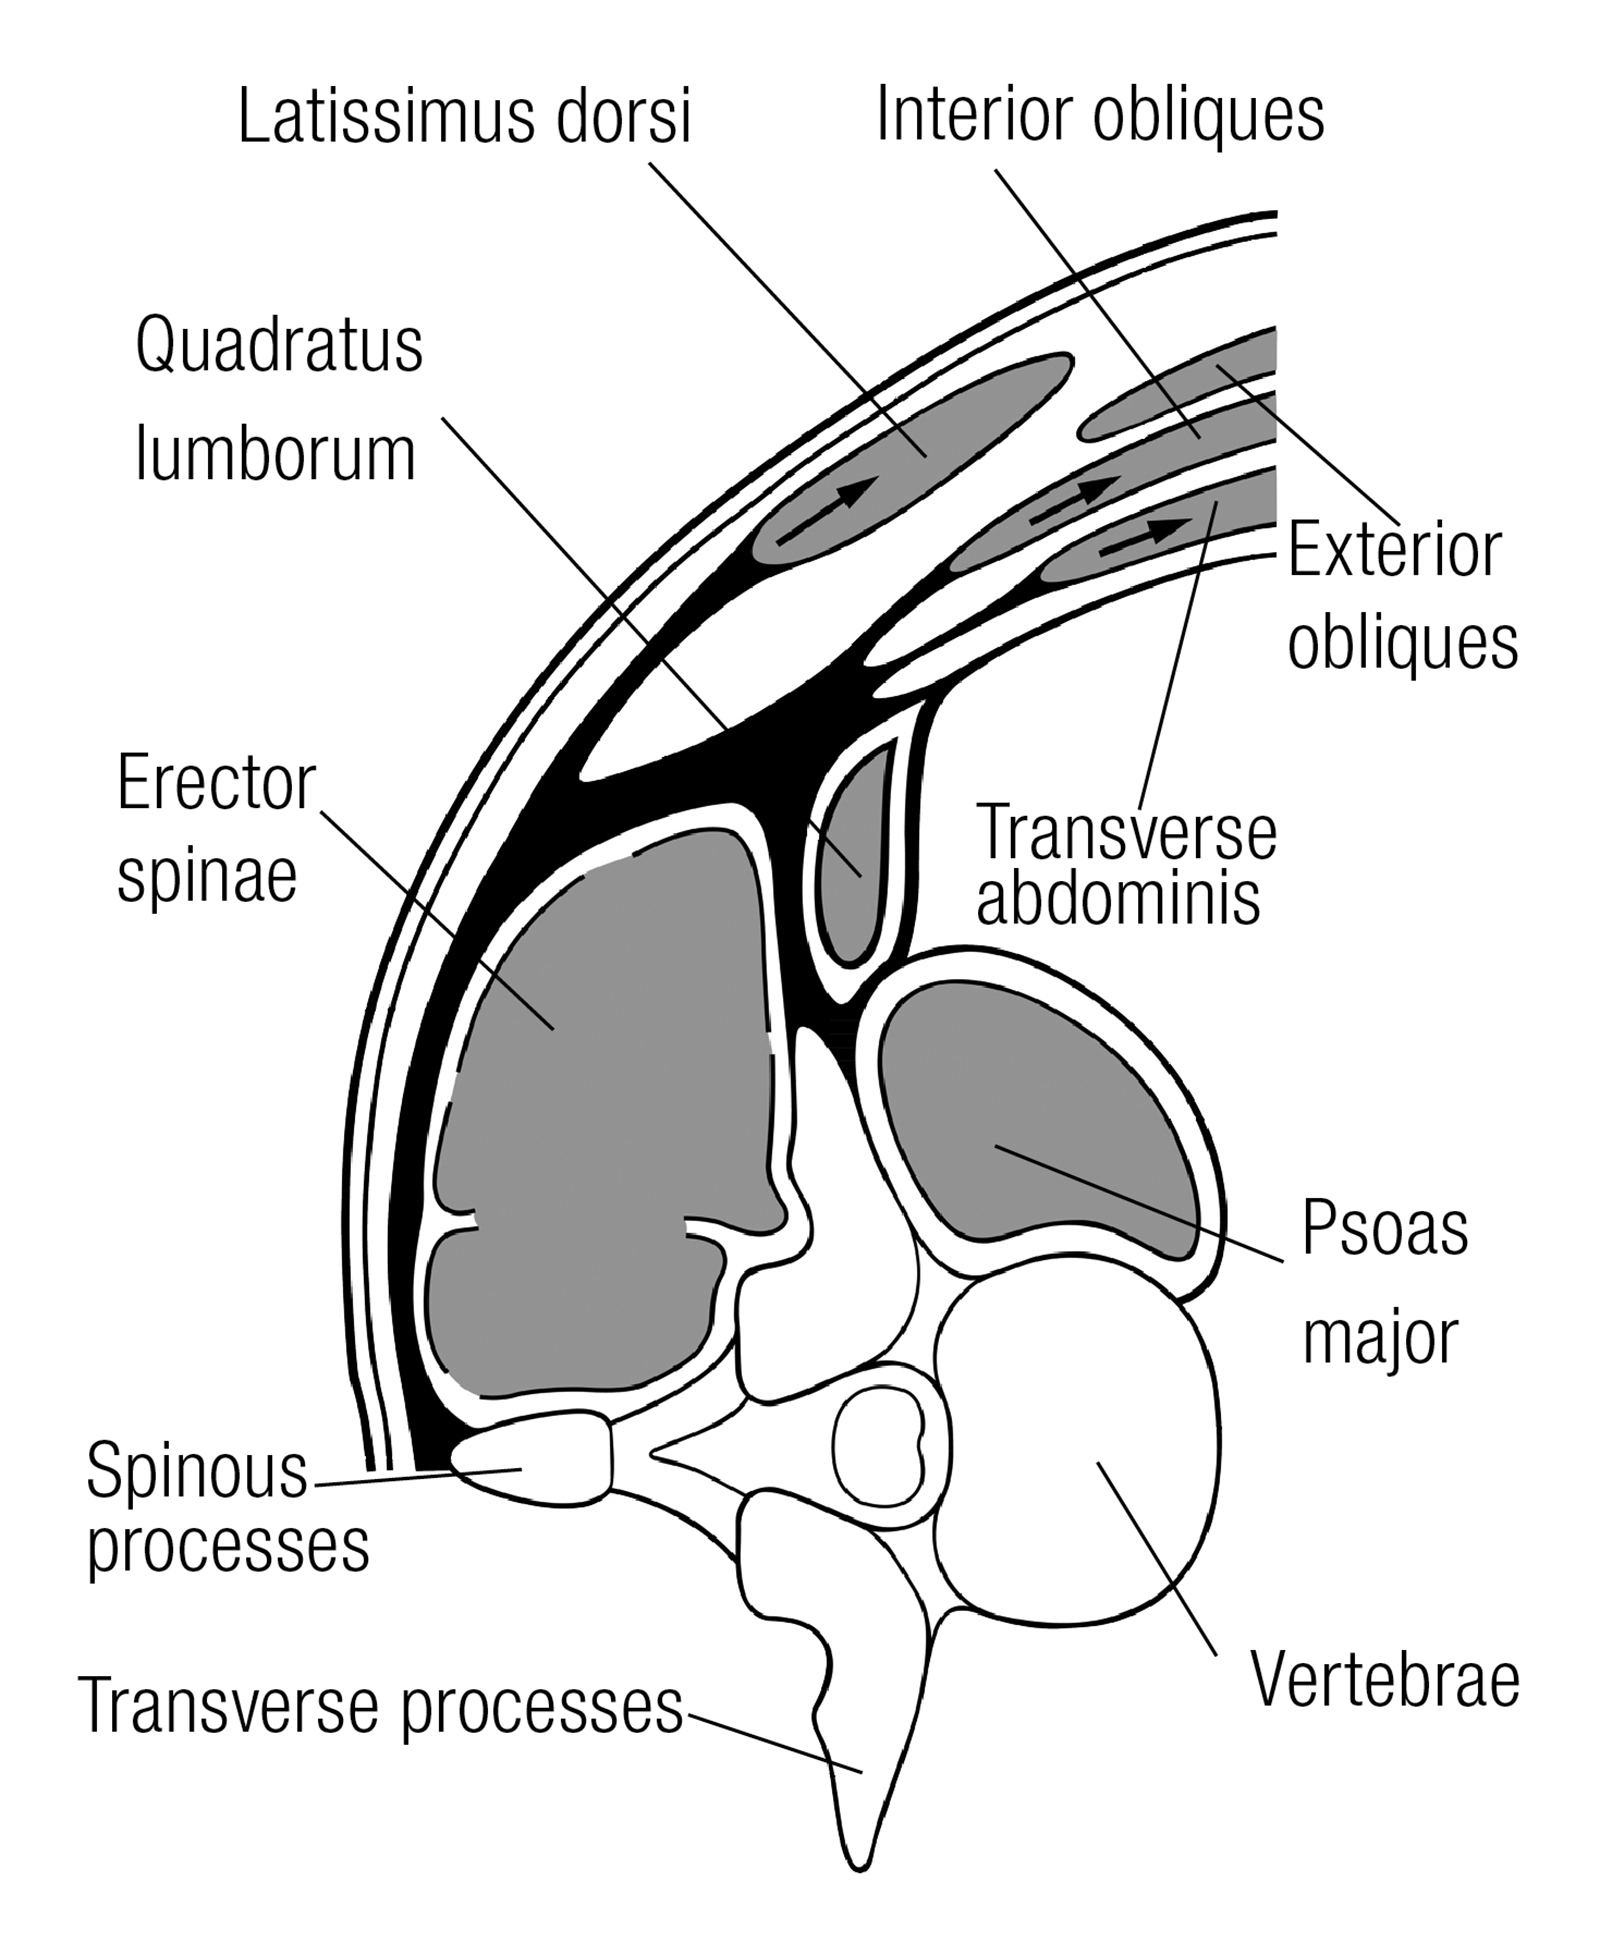
There are several outer layers in the low back, which include the posterior layer of the TLF. This layer covers the erector/multifidi group and gives rise to the latissimus dorsi that connects the back to the arm (Images 1 and 3).
Image 3.
Image 3.
Using a soft fist, sink into the space between the iliac crest and the 12th rib. Use a light touch so you can glide from the lateral to medial aspects of this space using slow, patient friction to move each layer in turn. Use no lubricant; the friction is the therapeutic tool that increases layer differentiation. Check with the client to make sure your pressure is comfortable—the TLF sub-layers are richly innervated and are sometimes more sensitive than the deeper layers underneath. Feel for increased tissue elasticity and increased gliding of one layer upon another. Repeat until you’ve worked the surface tissues between the pelvis and ribs.
Once you’ve prepared the outer layers with several lighter passes, ask your client for slow, active movement (“Let your knee slowly come toward your chest,” or “Very slowly, reach up above your head”). Make sure your client is breathing easily to broaden the effects of your work and evoke more powerful Golgi and nervous system responses.
Erector and Multifidus Layer
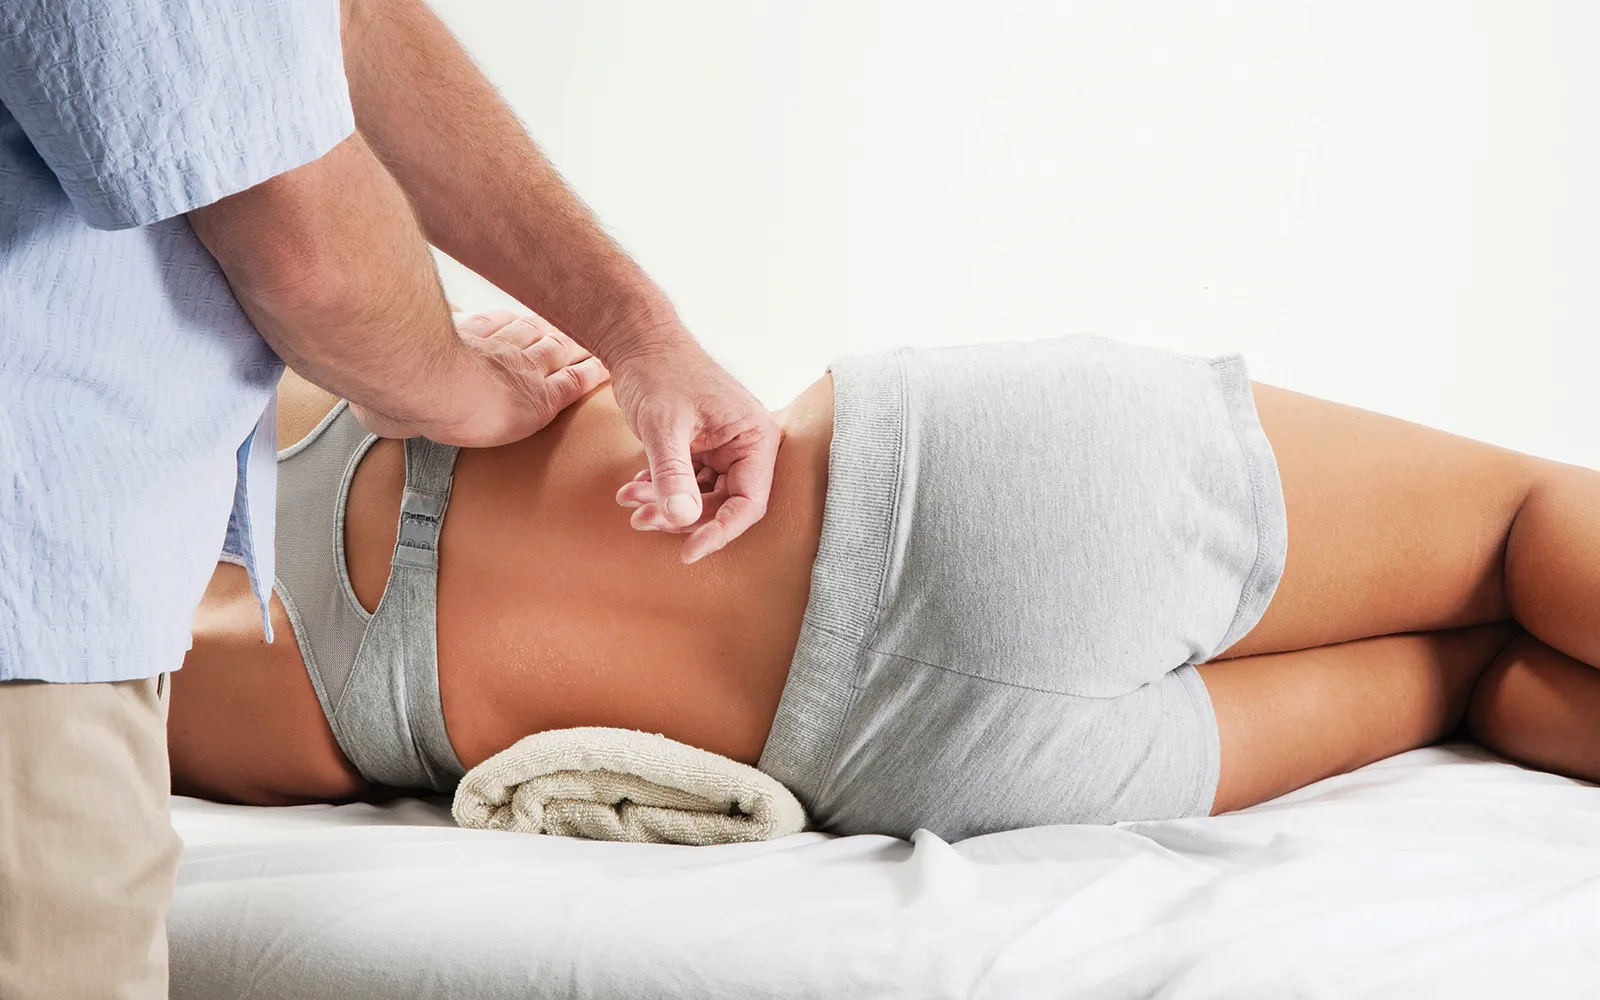
The spinal erectors and multifidi lie between the TLF’s posterior and middle layers. Many practitioners are accustomed to addressing the erectors posteriorly. With our client in a sidelying position, gravity enables a different approach. Use a soft fist to feel for the lateral edge of this large group of muscles, which will be several inches thick, and constitutes the bulk of the muscle mass next to the lumbar spine. Rather than sliding on the surface, sink into the thick lateral aspect of the erector group. Lower your table so you can stay above your client and use gravity to assist you.
If there is enough space between your client’s ribs and pelvis, you can carefully use your forearm to work the erector’s lateral aspects. Use the broad, flat surface of your ulna, being gentle and cautious; avoid using your elbow itself. If your client is uncomfortable with your pressure or pace, more preparation and a slower approach are indicated. Use your forearm to feel, rather than manipulate. Wait for a softening of this thick, muscular layer. Your touch is static, deep, and perceptive to evoke sensation and change, both within the muscles and their enveloping fasciae.
Image 4.
As a variation, ask your client for slow, active movement, as you did with the outer layers. This will move the fascia under your static touch and help facilitate neuromuscular reeducation as you coach your client to find new ways to initiate movement. At this level, movements must be slow and deliberate, since they will intensify your client’s sensations. Cue your client to make minute movements, as you work slowly and deeply.
Avoid putting pressure directly on the transverse processes, as overly aggressive lumbar work bruises the tissue by pushing it against the pointed processes. Know your client’s comfort level; don’t try to “rub away” any bumps or apparent knots—they might be bone.
Quadratus Lumborum Layer
The QL lies between the middle and anterior layers of the TLF, just anterior to the erectors. It is a key stabilizer of the trunk/pelvis relationship and is a postural muscle that is active in balancing, bending, breathing, and walking. The QL and the fascia around it can be a source of many kinds of back discomfort.
To find the QL and its fascia, use the Iliac Crest Technique to follow the crest medially until you encounter the attachments of the QL. Then, use your two thumbs together to isolate the QL layer. Don’t hyperextend your thumbs or apply excessive pressure; use static pressure and active client movements. Work the QL from its attachments on the iliac crest to its insertion on the 12th rib. Breathing and hip motions will be particularly relevant.
Image 5.Image 6.
Considerations
When properly applied, the work described here is safe and effective; however, some important considerations apply.
In sidelying work, be mindful of the ends of the floating ribs and the transverse processes of the vertebrae, which are sensitive and could be injured by incautious work.
These techniques are most effective with mild to moderate chronic back pain. Recent back injuries or surgery are contraindications until the tissues have healed (though with care, experienced practitioners can adapt these ideas for clients with recent back injuries). Older, healed injuries and surgeries often respond favorably to these techniques.
Strong low-back pain of sudden or frequent onset warrants referral to rehabilitation or complementary specialists, since such pain may need more care than most manual therapists typically provide.
Intervertebral disc issues (bulging, herniation, and degeneration) were long the favored explanation for many types of low-back pain. Recent research has shown this to be a relatively uncommon cause of pain; nevertheless, I do not recommend using these techniques on a client with disc issues until you are very familiar with their application and can reliably gauge pressure, duration, and response. One danger in working with disc issues is that those issues could be aggravated by releasing the client’s compensatory muscular and fascial tension too quickly or in an unbalanced way. Refer these clients to a specialist or work under a specialist’s close supervision until you’ve gained enough experience to competently address these issues.
Conclusion
At the beginning of this column, we listed some of the many mechanisms that have been thought to be responsible for back pain through the ages. While these factors may contribute to low-back pain, and their treatments may provide relief in individual cases, none of these theories has proven to be consistently effective with a majority of low-back pain sufferers. Our increased understanding of the TLF’s sensitivity and its role in back pain is a significant addition to our knowledge base, and it gives manual therapists new tools to help many clients’ back pain that has not responded to other treatments.
Notes
1. J. D. Frymoyer, “Back Pain and Sciatica,” New England Journal of Medicine 318 (1988): 291–300; Institute for Health Metrics and Evaluation, “2010 Global Burden of Disease Study.”
2. R. DonTigney, “The Sacroiliac Joint,” accessed July 2014, www.thelowback.com/history.htm; G. K. Lutz, M. Butzlaff, U. Schultz-Venrath, “Looking Back on Back Pain: Trial and Error of Diagnoses in the 20th Century,” Spine 28, no. 16 (2003): 1,899–905; D. C. Maharty, “The History of Lower Back Pain: A Look Back Through the Centuries,” Primary Care 39, no 3 (September 2012): 463–70; P. W. Hodges, C. A. Richardson, “Inefficient Muscular Stabilisation of the Lumbar Spine Associated with Low Back Pain: a Motor Control Evaluation of Transversus Abdominis,” Spine 21, no. 22 (1996): 2,640–50; L. A. Danneels et al., “CT Imaging of Trunk Muscles in Chronic Low Back Pain Patients and Healthy Control Subjects,” European Spine Journal 9, no. 4 (2000): 266–72.
3. R. Deyo and J. Weinstein, “Low Back Pain,” New England Journal of Medicine 344 (2001): 363–70.
4. H. M. Langevin et al., “Ultrasound Evidence of Altered Lumbar Connective Tissue Structure in Human Subjects with Chronic Low Back Pain,” BMC Musculoskeletal Disorders 10 (2009): 151.
5. H. M. Langevin et al., “Reduced Thoracolumbar Fascia Shear Strain in Human Chronic Low Back Pain,” BMC Musculoskeletal Disorders 12 (2011): 203;. A. D. Furlan et al., “Massage for Low-Back Pain,” Cochrane Database of Systematic Reviews 4 (2008): CD001929.
6. P. Nickelston, “Thoracolumbar Fascia: The Chronic Pain Linchpin,” Dynamic Chiropractic 31, no. 21 (2013); T. Myers, Anatomy Trains (Churchill Livingstone, 2009).
7. R. Schleip, “Fascial Plasticity—A New Neurobiological Explanation, Part I,” Journal of Bodywork and Movement Therapies 7, no. 1 (2003): 14.
To understand tissue-tension barriers, MTs must be constantly present and mindful. Too light and we will not become efficient at creating the healing change that is needed.